Sacroiliac (SI) joint pain is less common than general low back pain, but it shows up more often in specific groups: pregnant and postpartum patients, and anyone recovering from a fall or direct trauma to the pelvis. It’s also one of the harder diagnoses to pin down, which is part of why treatment approaches vary so much between providers.
Why SI Joint Pain Is Tricky to Diagnose
Roughly 13% of patients with low back pain have their symptoms traced back to the SI joint, though estimates across studies range from 9% to 26% (Maigne et al., 1996). When it is the SI joint, the pain pattern is fairly consistent: buttock pain shows up in 94% of cases, lower lumbar pain in 72%, pain radiating into the leg in 50%, and groin pain in 14% (Slipman et al., 2000).
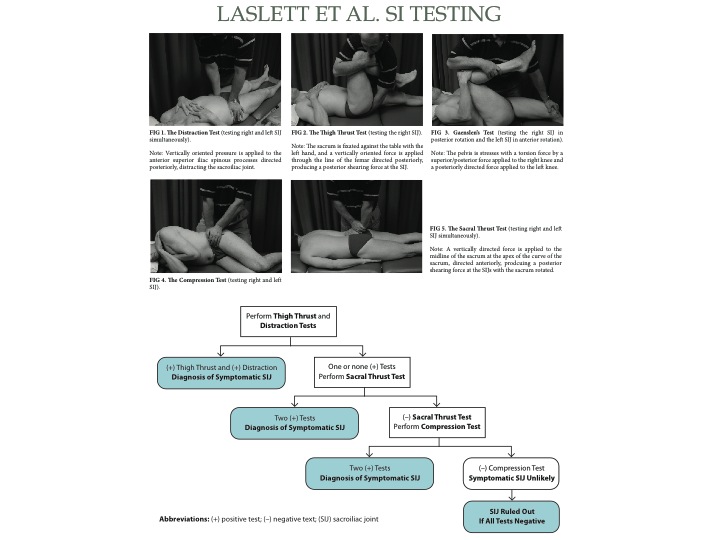
The diagnostic challenge is that the clinical tests used to identify SI joint involvement, static palpation and movement-based provocation tests, also come back positive in people with no symptoms at all, which limits how much any single test can tell you (Dreyfuss et al., 1994). For more on just how unreliable these individual tests can be, see our review of SI joint test reliability.
Because no single test is reliable on its own, a thorough evaluation typically starts by ruling lumbar spine involvement in or out before moving to SI-specific provocation testing.
What Actually Helps
The most effective approach to SI joint pain isn’t a single technique. It’s a combination: manual therapy (mobilization or manipulation), taping, targeted strengthening, and proprioception training, matched to what the evaluation actually finds.
On manipulation specifically: a classic imaging study found that manipulation reduced pain and improved movement without changing the position of the sacrum or ilium on imaging, meaning the improvement isn’t coming from “putting the joint back into place.” We cover that study, and what the mechanism actually looks like, in more detail in SI joint manipulation works, just not how you think.
Manipulation also shows strong outcomes for a specific subgroup of low back pain patients. A clinical prediction rule developed by Flynn and colleagues identified which patients are most likely to respond well to manipulation, and a follow-up validation study by Childs and colleagues confirmed those patients see meaningfully better outcomes with manipulation plus exercise than with exercise alone.
Exercise matters just as much for keeping symptoms from coming back. In a trial comparing specific stabilization training to standard medical management, patients who did the targeted exercise program had a substantially lower rate of recurrence over three years than those who received usual care alone (Hides et al., 2001). There’s no strong evidence that more general “core” or “global” stabilization work outperforms a more localized, targeted approach for patients who fit this profile.\


When It’s Time to See a Physical Therapist
If you’re dealing with low back pain, pelvic pain, or groin pain and suspect your SI joint is involved, particularly if it started during pregnancy, postpartum, or after a fall, it’s worth getting evaluated rather than waiting it out. Early manual therapy and exercise consistently lead to better short- and long-term outcomes than delaying treatment.
If SI joint pain is limiting your daily activity or training, an evaluation that looks at the full picture, not just one test, is the right next step. Book an SI joint evaluation at Mend’s Boulder or Lafayette clinic.
Browse more of our sacroiliac joint pain coverage, or see the full Orthopedic Care library.
References
1. Maigne, J. et al. Results of Sacroiliac Joint Double Block and Value of Sacroiliac Pain Provocation Tests in 54 Patients With Low Back Pain. Spine. 1996. 21(16):1889-1892
2. Dreyfuss, P et al. Positive sacroiliac tests in asymptomatic adults. Spine. 1994. 19:1138-1143,
3. Slipman CW. et al. Sacroiliac joint pain referral zones. Arch Phys Med Rehab. 2000;8 1:334-8.
4. Tullberg, T. et al. Manipulation Does Not Alter the Position of the Sacroiliac Joint: A Roentgen Stereophotogrammetric Analysis. Spine. 1998. 23(10):1124-1128.
5. Flynn, T et al. A clinical prediction rule for classifying patients with low back pain who demonstrate a short term improvement with spinal manipulation. Spine. 2002; 27(24):2835-2843.
6. Childs, J. Fritz, J. et al. A Clinical Prediction Rule To Identify Patients with Low Back Pain Most Likely To Benefit from Spinal Manipulation: A Validation Study. Annals of Int Med. 2004/920-928.
7. Hides, J. et al. Long-Term Effects of Specific Stabilizing Exercises for First-Episode Low Back Pain. Spine. 2001. 26(11):243-248.
8. Koumantakis, G. et al. Trunk Muscle Stabilization Training Plus General Exercise Versus General Exercise Only: Randomized Controlled Trial of Patients With Recurrent Low Back Pain. Phys Ther. 2005;85:209 –225