If rolling over in bed, climbing stairs, or standing on one leg to pull on your pants sends a sharp pain into the back of your pelvis or the front of your pubic bone, you are probably dealing with pelvic girdle pain. It is the most common musculoskeletal complaint of pregnancy, and it responds to physical therapy.
The 2017 clinical practice guideline from the American Physical Therapy Association’s women’s health and orthopedic sections (Clinton et al.) estimates that 56% to 72% of pregnant people have pelvic or low back pain at some point, with the highest rates late in pregnancy. Common does not mean you have to wait it out.
Where pelvic girdle pain shows up
Pelvic girdle pain sits in the joints that make up the ring of the pelvis: one or both sacroiliac (SI) joints at the back, the pubic symphysis at the front, or both. Pain often spreads into the buttock, groin, or inner thigh. It tends to flare with single-leg tasks and with movements where the legs go in different directions, like getting out of a car, climbing stairs, or turning over in bed.
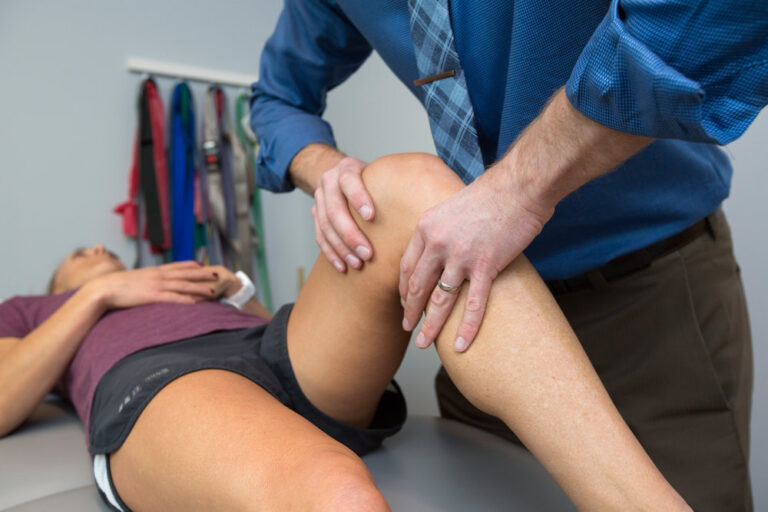
A physical therapist confirms it with a handful of provocation tests rather than a single one. The guideline summarizes the tests with the best accuracy in pregnancy: the posterior pelvic pain provocation test (thigh thrust), the active straight leg raise, the FABER test, and palpation of the pubic symphysis when the pain is in front. Hip and low back problems can look similar, so they get checked at the same time. If the pain is mostly at the front, our article on relieving pubic symphysis pain during pregnancy goes into that version in more detail.
Who is more likely to have it, and to keep it
The guideline lists a prior pregnancy, a history of hip or low back problems, smoking, a higher BMI, job dissatisfaction, and a belief that the pain will not improve as risk factors.
Pain that starts early in pregnancy, shows up in several places at once, or produces several positive tests is more likely to persist into late pregnancy. That is the main reason the guideline recommends starting treatment soon after symptoms begin, and why we encourage people to see a pelvic health physical therapist during pregnancy instead of waiting for delivery to fix it.
Manual therapy for pelvic girdle pain
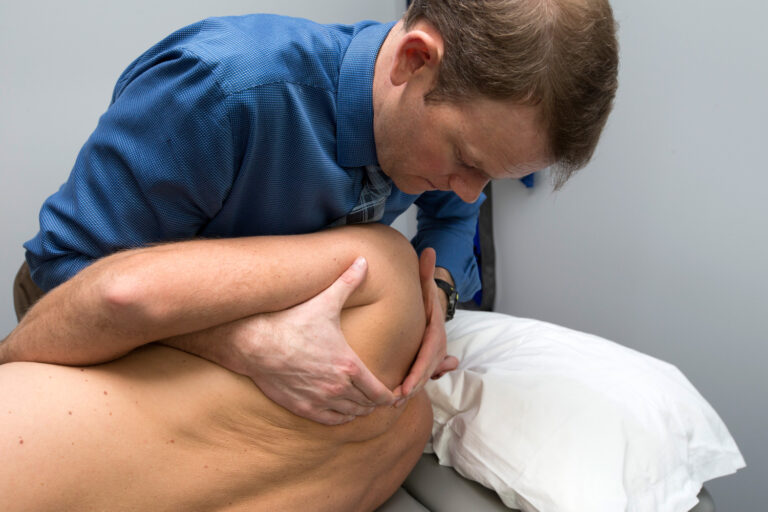
Manual therapy means hands-on treatment: joint mobilization, manipulation, and soft tissue work. For pelvic girdle pain, it usually targets the SI joints, the low back, and the muscles that guard the pelvis, including the glutes, the deep hip rotators, and the adductors along the inner thigh.
Safety is the first question most pregnant patients ask. The guideline found no reported adverse events from manual therapy in healthy pregnant patients and lists high-velocity, low-amplitude manipulation as an acceptable option. Its rating of the evidence for benefit is a cautious “may or may not use,” because the trials are still small. In practice, manual therapy earns its place by lowering pain quickly enough that you can sleep, walk, and exercise. It is rarely the whole plan.
During pregnancy, treatment is adapted to your body. Most techniques are done side-lying or seated with pillow support, and force is graded to what feels comfortable. Many patients notice the change right away, in how easily they can roll over or step up onto a stair.
One misconception is worth clearing up. Manipulation does not put a pelvis “back in place.” An imaging study by Tullberg and colleagues tracked SI joint position with bone markers and found it unchanged after manipulation, even in patients whose symptoms improved. The relief comes from how the nervous system and surrounding muscles respond, which we cover in SI joint manipulation works, just not how you think.
Exercise and daily movement
The guideline recommends exercise for pelvic girdle pain and leaves the specific program to the clinician. Early on, the goal is calming things down: cutting back on the movements that provoke pain, such as long strides, deep single-leg lunges, or standing on one leg to dress. From there, we reintroduce those movements gradually and build strength in the hips, glutes, abdominals, and pelvic floor.
Small changes to daily mechanics help more than people expect. Keeping the knees together when you roll over or get out of the car, sitting down to put on pants and shoes, and taking stairs one step at a time all reduce the shearing load through the pelvis.
Support belts
The guideline recommends considering a pelvic support belt, while noting the evidence is mixed. In our experience, a belt is worth a short trial. People who benefit tend to feel it within minutes, so you find out quickly whether it is worth wearing. A belt is most useful for walking and long periods of standing, and works best alongside exercise.
Posture and relaxin are not the cause
Two explanations still circulate. The first is posture. The increased arch in the low back and forward tilt of the pelvis are normal changes in pregnancy, and the guideline advises against treating their size as a sign of how severe pelvic girdle pain is or will become.
The second is relaxin, the hormone often blamed for loose joints. Current studies show no link between relaxin levels and pelvic girdle pain. That matters because “your joints are too loose” can make people afraid to move, and staying active is a large part of getting better.
Pelvic girdle pain after delivery
For most people, pelvic girdle pain eases in the weeks and months after birth. For some it does not. A Swedish cohort study (Bergström et al., 2017) followed women whose pelvic girdle pain continued after pregnancy, and 12 years later about 40% of those who responded still reported pain. Pain that lasted longer or showed up in other areas, like the neck or upper back, predicted a worse long-term outcome. If your pain is still limiting you a few months after delivery, it deserves a proper assessment, not more waiting.
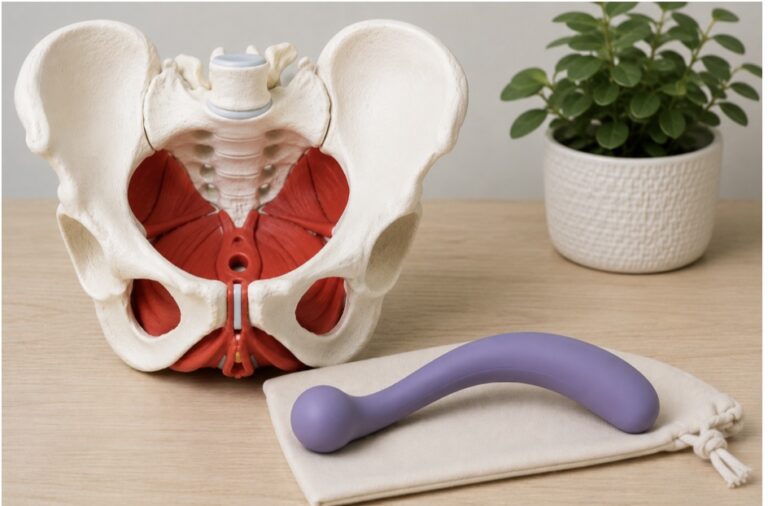
One postpartum complaint we hear often is pain at the base of the spine or tailbone when lying flat for mat exercises like bridges, marches, and pelvic tilts. During a vaginal delivery, the tailbone (coccyx) moves backward to open the pelvic outlet. The deep pelvic floor muscle that attaches to it, the coccygeus, can stay tight and sore afterward, and lying on a hard surface presses right on that area.
Manual therapy helps here too. Gentle mobilization of the sacrum and tailbone, along with soft tissue work to ease tension in the coccygeus and surrounding muscles, usually makes floor exercise tolerable again. We then build back into mat work and loaded exercise in stages. For some postpartum patients with low back and pelvic pain, dry needling is another option that pairs well with exercise.
When to get it checked
Book an evaluation if pelvic pain is limiting your sleep, walking, or work, if it started early in pregnancy, or if it is still around a few months after delivery. Some symptoms need a closer look: pain that keeps getting worse despite rest and modification, or deep hip or groin pain with weight bearing. Pregnancy lowers bone density, and in rare cases transient osteoporosis of the hip can lead to a stress fracture.
Our pelvic health and SI joint physical therapists treat pelvic girdle pain with manual therapy, exercise, and practical changes to how you move through your day, during pregnancy and after. If standing on one leg, rolling over in bed, or lying on the floor for a workout hurts, book an appointment at our Boulder or Lafayette clinic.
References
Clinton SC, Newell A, Downey PA, Ferreira K. Pelvic Girdle Pain in the Antepartum Population: Physical Therapy Clinical Practice Guidelines Linked to the International Classification of Functioning, Disability, and Health From the Section on Women’s Health and the Orthopaedic Section of the American Physical Therapy Association. Journal of Women’s Health Physical Therapy. 2017;41(2):102-125. https://doi.org/10.1097/JWH.0000000000000081
Bergström C, Persson M, Nergård KA, et al. Prevalence and predictors of persistent pelvic girdle pain 12 years postpartum. BMC Musculoskeletal Disorders. 2017;18(1):399. https://doi.org/10.1186/s12891-017-1760-5