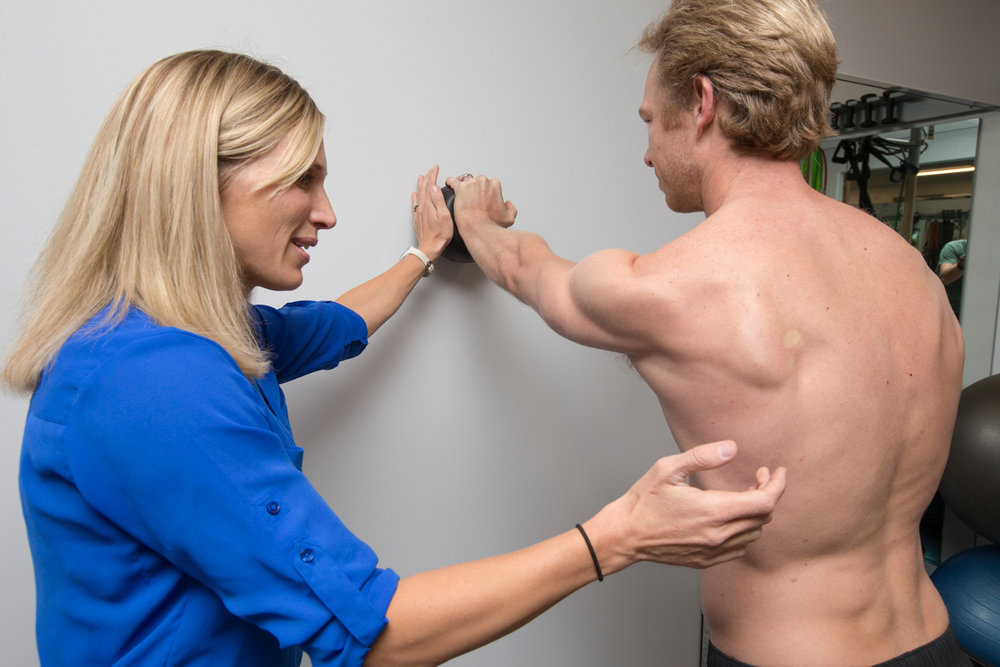
If your shoulder pinches when you press overhead, reach for a high hold, or roll onto it at night, there’s a good chance someone has called it impingement. It’s the most common diagnosis behind shoulder pain, and it is also one of the most treatable without surgery. The research points to a consistent plan: specific exercise as the foundation, with manual therapy added early to calm pain and get you training again sooner.
What Shoulder Impingement Actually Means

Impingement describes pain at the top or outside of the shoulder as the arm rises, usually worst somewhere between 60 and 120 degrees of elevation. Clinicians call this the painful arc. The original explanation was mechanical: the rotator cuff tendons and the subacromial bursa get pinched between the head of the humerus and the acromion above it.
That model turns out to be less tidy than it sounds. The shape of the acromion doesn’t reliably predict who has pain, and in the CSAW trial (Beard and colleagues, The Lancet, 2018), surgically shaving bone off the acromion did no better than an arthroscopy that removed nothing at all. For that reason, many clinicians now prefer the terms subacromial pain syndrome or rotator cuff related shoulder pain. The label overlaps heavily with rotator cuff tendinopathy, and pain at the front of the shoulder is sometimes the biceps tendon instead. Our breakdown of biceps tendinopathy vs. impingement covers how to tell them apart.
What matters for treatment is simpler. The tissues at the top of the shoulder are irritated and not tolerating the load you’re putting through them. That usually traces back to things physical therapy can change: rotator cuff and scapular strength, thoracic and shoulder mobility, and how quickly overhead volume has climbed in your training.
Waiting it out isn’t a reliable plan. Shoulder pain affects up to 47% of adults over the course of a year (Luime and colleagues, 2004), and roughly half of new shoulder complaints are still unresolved six months later (Winters and colleagues, 1999).
Exercise Comes First
Specific, progressive exercise has the strongest support of any treatment for impingement. Steuri and colleagues (British Journal of Sports Medicine, 2017) reviewed 177 studies and concluded that exercise should be the first treatment offered. Exercises targeted to the patient’s specific impairments outperformed generic shoulder programs. A 2020 update by Pieters and colleagues in JOSPT, which pooled 16 systematic reviews on subacromial shoulder pain, reached the same conclusion for both short- and long-term pain and disability. The same review found that passive modalities such as ultrasound, laser, and shockwave added little.
In practice, that means loading the rotator cuff (external rotation in particular) and the muscles that control the shoulder blade, such as serratus anterior and lower trapezius. Exercises start in ranges that don’t provoke symptoms and progress toward the positions your sport demands. For a climber, the program ends with hangs and overhead pulls. For a lifter, it ends with pressing and overhead holds under real load.
Exercise also holds up against surgery. Brox and colleagues (BMJ, 1993) found supervised exercise as effective as arthroscopic subacromial decompression for stage II impingement. A 2019 review of 11 randomized trials found no difference in outcomes between physical therapy and surgery for impingement, even at long-term follow-up.
Where Manual Therapy Fits
Manual therapy doesn’t replace exercise. It makes the exercise possible sooner. In a randomized trial of patients with impingement, Bang and Deyle (JOSPT, 2000) found that manual therapy plus supervised exercise produced greater improvements in pain, function, and strength than the same exercise program alone. Smaller trials from Senbursa (2007) and Kachingwe (2008) reported similar results, and both the Steuri and Pieters reviews support adding manual therapy to exercise for short-term pain relief.
The effect on recovery time is the most practical finding. Bergman and colleagues (Annals of Internal Medicine, 2004) added manipulative therapy to usual medical care for patients with shoulder pain and dysfunction. Patients who received usual care alone took 52 weeks to reach the level of improvement the manual therapy group showed at 12 weeks.
At the shoulder itself, treatment usually means graded joint mobilizations to the glenohumeral joint, scapula, and clavicle to restore motion that pain has taken away. We cover what those techniques involve in our guide to shoulder manipulation in physical therapy.
Why We Treat the Upper Back
Raising your arm overhead requires the thoracic spine to extend and rotate. When the upper back is stiff, the shoulder blade has to compensate, and the tissues under the acromion absorb more of the load. Boyles and colleagues (Manual Therapy, 2009) applied thoracic spine thrust manipulation to patients with shoulder impingement and found significant drops in pain and disability within 48 hours. Treating an area away from the painful one is called regional interdependence, and we explain it further in thoracic manipulation and shoulder pain.
What a Treatment Plan Looks Like
The first visit is an assessment. We look at where in the arc your pain shows up, test rotator cuff strength and scapular control, check thoracic and shoulder mobility, and ask about your training load. That exam is what separates impingement from a tendinopathy, a biceps problem, or a rotator cuff tear that needs a different plan.
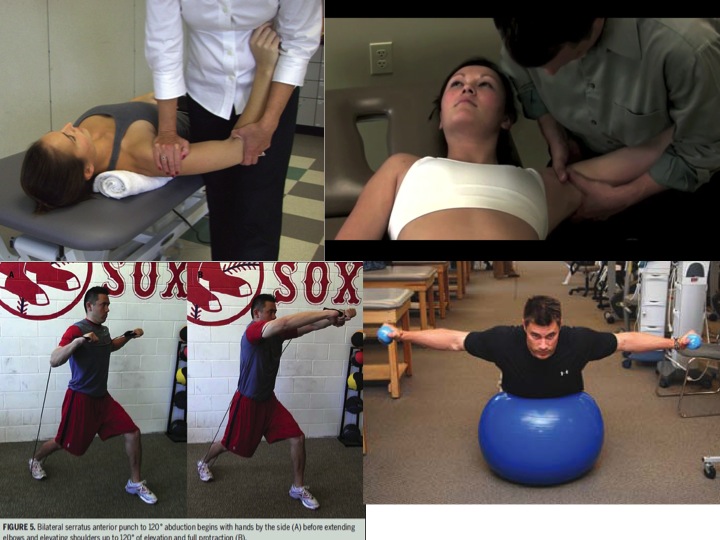
Early sessions pair manual therapy with exercise in the same visit. The hands-on work opens a window of less pain and more motion, and we load exercise into that window so the gains carry over. You keep training through this phase, with changes. A landmine press might replace a strict overhead press for a few weeks, or a climber might cut hang volume while keeping easier terrain.
As symptoms settle, manual therapy tapers and loading increases toward the specific demands of your sport or job. Most people notice meaningful change within the first few weeks of consistent work. Returning to heavy overhead training usually takes longer, often around three months.
Getting Started
If overhead pressing, climbing, or sleeping on your side has been painful for more than a few weeks, an evaluation will sort out whether you’re dealing with impingement or something else and get you on a plan that keeps you training. You can read how we approach shoulder pain treatment and manual therapy, or book an evaluation. For more research on the topic, browse our articles on the shoulder and on manual therapy.
Frequently Asked Questions
Yes, in most cases. Supervised exercise has matched subacromial decompression surgery in randomized trials, and the CSAW trial found decompression no better than a placebo arthroscopy. Surgery is generally reserved for people who don’t improve after a full course of physical therapy or who have a structural injury such as a significant rotator cuff tear.
Most people notice meaningful improvement within the first few weeks of consistent exercise. A full return to heavy overhead lifting or climbing usually takes around three months. Adding manual therapy to exercise has been shown to shorten recovery compared with usual care alone.
Usually not. Complete rest tends to leave the shoulder weaker and less tolerant of load when you return. A physical therapist can help you swap or scale the movements that provoke pain while you keep training everything else.
They overlap heavily. Impingement describes where and when the pain occurs, while rotator cuff tendinopathy describes the irritated tendon that is often the source. Treatment for both is built on progressive rotator cuff and scapular strengthening.
References
- Bang MD, Deyle GD. Comparison of supervised exercise with and without manual physical therapy for patients with shoulder impingement syndrome. J Orthop Sports Phys Ther. 2000;30(3):126-137.
- Beard DJ, et al. Arthroscopic subacromial decompression for subacromial shoulder pain (CSAW): a multicentre, pragmatic, parallel group, placebo-controlled, three-group, randomised surgical trial. Lancet. 2018;391:329-338.
- Bergman GJ, et al. Manipulative therapy in addition to usual medical care for patients with shoulder dysfunction and pain: a randomized, controlled trial. Ann Intern Med. 2004;141:432-439.
- Boyles RE, et al. The short-term effects of thoracic spine thrust manipulation on patients with shoulder impingement syndrome. Man Ther. 2009;14:375-380.
- Brox JI, et al. Arthroscopic surgery compared with supervised exercises in patients with rotator cuff disease (stage II impingement syndrome). BMJ. 1993;307(6909):899-903.
- Kachingwe AF, Phillips B, Sletten E, Plunkett SW. Comparison of manual therapy techniques with therapeutic exercise in the treatment of shoulder impingement: a randomized controlled pilot clinical trial. J Man Manip Ther. 2008;16:238-247.
- Kuhn JE. Exercise in the treatment of rotator cuff impingement: a systematic review and a synthesized evidence-based rehabilitation protocol. J Shoulder Elbow Surg. 2009;18:138-160.
- Luime JJ, et al. Prevalence and incidence of shoulder pain in the general population; a systematic review. Scand J Rheumatol. 2004;33:73-81.
- Michener LA, et al. Effectiveness of rehabilitation for patients with subacromial impingement syndrome: a systematic review. J Hand Ther. 2004;17:152-164.
- Nazari G, et al. Effectiveness of surgical vs. conservative interventions for subacromial impingement syndrome: a systematic review and meta-analysis. PLoS One. 2019.
- Pieters L, et al. An update of systematic reviews examining the effectiveness of conservative physical therapy interventions for subacromial shoulder pain. J Orthop Sports Phys Ther. 2020;50(3):131-141.
- Senbursa G, et al. Comparison of conservative treatment with and without manual physical therapy for patients with shoulder impingement syndrome: a prospective, randomized clinical trial. Knee Surg Sports Traumatol Arthrosc. 2007;15:915-921.
- Steuri R, et al. Effectiveness of conservative interventions including exercise, manual therapy and medical management in adults with shoulder impingement: a systematic review and meta-analysis of RCTs. Br J Sports Med. 2017;51:1340-1347.
- Tate AR, et al. Comprehensive impairment-based exercise and manual therapy intervention for patients with subacromial impingement syndrome: a case series. J Orthop Sports Phys Ther. 2010;40:474-491.
- Winters JC, et al. The long-term course of shoulder complaints: a prospective study in general practice. Rheumatology. 1999;38:160-163.